When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Since the introduction of Anti-retroviral Therapy (ART), there has been a significant reduction in the mortality associated with Human Immunodeficiency Virus (HIV)[1]. As a result more people are living with HIV as a chronic condition, and this has necessitated an increased focus on factors affecting morbidity. Pain is one such a factor that has been shown to negatively affect the quality of life and function of people living with HIV (PLWH)[2][1].
The prevalence of pain among PLWH vary among populations. Parker et al. (2014)[2] found that pain (mostly moderate to severe) is reported in 54-67% of PLWH. In later studies, high variability in frequencies were found, but most reported a pain prevalence of more than 50%[1]. It is clear that pain is a prominent concern in PLWH, and it remains poorly controlled and undertreated in this population[2][3].
Impact of Pain
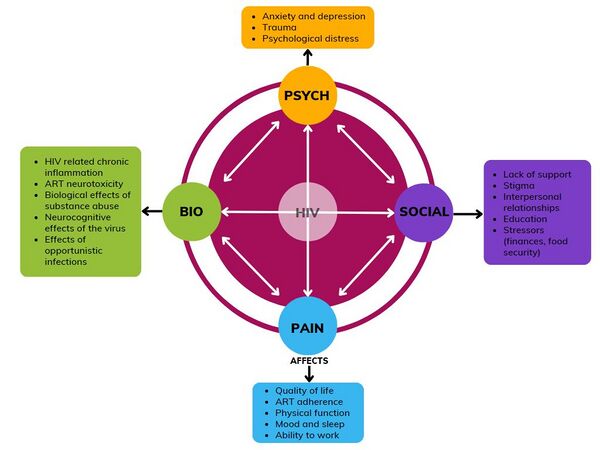
Untreated and poorly managed pain can be very debilitating. In PLWH it has been shown to have significant negative effects on the following:
This clearly demonstrates the importance of addressing pain in PLWH in order to limit its impact on quality of life and function[2]. Although the current WHO HIV package of care guidelines recommend psychosocial counselling and support[6], there is a need to included screening and treatment of chronic pain in order to comprehensively manage PLWH.
Factors Contributing to Pain
The following factors have been found to increase the risk of pain in PLWH:
Depression and anxiety[2] - Depression has specifically been associated with greater intensity in pain in PLWH and is very common in PLWH[7][8][4]
Stigma - Although common in PLWH, there is a lack of evidence on the effect of stigma on pain[4]
The African Context
Studies measuring physical activity in PLWH in the US/EU have found that pain in the population results in significant physical impairment - this however is not the case in the African context, were little to no functional interference occurs[9]. A study conducted in SA concluded that stigma and family responsibilities may drive patients to push through despite pain[9].
Common Pain Conditions
Zhu et al. studied symptom clusters in PLWH, and found "numbness, muscle aches, and joint pain" to be the fourth most common symptom cluster[8]
Peripheral Neuropathy: More than one-third of PLWH suffer from HIV-neuropathy, with some studies reporting incidence rates of up to 66%[7][4]. Of those with neuropathy, 38-78% experience painful neuropathy (neuropathic pain)[7][4]
Spinal Pain:Low back pain or neck pain is present in 1% to 55% of PLWH[1]
Lower extremity pain: present in 3-58% of PLWH, most commonly affecting the feet and legs[1]
Joint Pain: Osteoarthritis is present in 2-50% of PLWH[1]
Upper and extremity pain: present in 2-5% of PLWH, mostly involving the hands and shoulders[1]
Pain Mechanisms in HIV
PLWH can present with complex pain conditions as a result of the virus itself, or as a side-effect of ART. It can be useful to consider the possible pain mechanisms involved in order to provide targeted treatment.
Neurotoxicity caused by the HIV-1 glycoprotein (infects Schwann cells and neurons)
Neurotoxicity caused by certain anti-retroviral drugs (causes mitochondrial dysfunction)[10][11]. Nucleoside analogue-transcriptase inhibitors (NRTIs) (Zidovudine, didanosine, stavudine, lamivudine and abacavir) have be closely linked with severe peripheral neuropathy[10] - Stavudine-based anti-retroviral drugs should be phased out for this reason[10]
Regardless of the cause, symptoms and clinical signs are similar and include distal polyneuropathy with paraesthesia and may involve hyperalgesia and allodynia[7]
Nociceptive pain
Tissue damage can occur with an injury. PLWH tend to have elevated inflammatory cytokines, which could result in an amplified pain response following tissue damage[12][11]
Elevated inflammatory cytokine are associated with increasing age[11]
Chronic Nociplastic pain
Chronic pain is influenced by a range of immunological and psychosocial factors[3]
The stigma associated with HIV, as well as the high prevalence of depression and anxiety, can negatively modify pain-pathways resulting in persistent pain[4]
Fear-avoidance could potentially influence pain in PLWH and required further research[4]
Various studies have failed to identify drugs that have proven effectiveness in reducing pain (especially neuropathic pain) in PLWH[10]. The South African Medical Research Council has reported that there is an "absence of empirical evidence supporting efficacy of pharmacological agents typically recommended for the management of neuropathic pain in this population group" [13]
ART
There is no correlation between ART and pain reduction, which indicates that treatment of the virus alone is not effective in managing pain in PLWH[2]
Neuropathic Pain Medication
Medications often used to treat neuropathic pain have not been effective in relieving HIV related neuropathic pain - these include anti-depressants, anticonvulsants, topical agents, opioids and non-steroidal anti-inflammatories (NSAIDs)[14][10][4].
Other
Cannabis: There is some evidence that smoking cannabis has a positive effect on neuropathic pain in PLWH, by activating the endocannabinoid system (ECS)[14][7]. It is however not recommended as a feasible option for pain management, as HIV is a chronic condition and the long-term use of smoked cannabis can have negative psycho-active effects. The research does however suggest that targeting cannabinoid receptors may be an effective approach in managing neuropathic pain in PLWH. Non-psychoactive cannabinoids administered via other routes would be more suitable and require further research[14].
Topical capsaicin: There is some evidence of a short term positive effect on pain in PLWH[7][10].
Non-Pharmacologic
Non-pharmacological interventions seem the hold the most promise in addressing HIV related pain. There is however still a great need for further, high-quality research to determine which interventions are superior and the most cost-effective and feasible in different contexts[7].
Exercise
A recent systematic review on neuropathic pain concluded that both aerobic exercise and progressive resistance exercise is superior to usual care (including education) in treating neuropathic pain in PLWH in low- and middle income countries (LMICs)[15][16][17].
The frequency of exercise shown to be effective is 30-60min, 3 times per week for 12 weeks[15][16][17].
One study conducted a follow-up 12 weeks after the intervention ended, and found that continued home exercises resulted in sustained reduction in pain[16].
Exercise seems to be less effective if it is initiated >7 years after diagnosis[16].
Relaxation: Yoga, relaxation strategies and mindfulness may provide benefits, especially when anxiety and depression are present
Cognitive Behavioural Therapy (CBT): A recent systematic review found that CBT can result in significant reductions in neuropathic pain intensity[7].C CBT can be very useful to identify behaviours that could be making pain worse (e.g. avoiding activity) and to work on coping strategies[11]
Supportive Psychotherapy: Effectiveness is comparable with CBT, for neuropathic pain[7]
A recent systematic review found that there is limited evidence to suggest that "self-management interventions (delivered either online, face-to-face or group-based with a booklet) are effective in improving pain, physical symptoms and quality of life in PLWH with chronic pain"[5].
The Positive Living Workbook is a 6-week peer-led exercise and education intervention that was developed by Romy Parker. It offers a multimodal intervention for pain by incorporating education, exercise, CBT and self-management strategies[18][3]. Two studies that utilised this workbook demonstrated a significant reduction in pain interference and improvement in function in women living with HIV[3][19].
Turner et al utilised a similar programme, named Living Better Beyond Pain. Education sessions were offered monthly over 6 months. Pain was not measured, but the intervention resulted in significant improvements in physical function (note that this study also included people without HIV)[20].
A study conducted in Malawi, found that a single educational session with carers and late-stage HIV patients resulted in improvements in pain. These sessions focused on HIV related pain, myths about pain and management strategies[21].
Therapeutic Relationship
Jackson et al. found that a good therapeutic relationship (established by frequent communication in one's home-language with an caring research assistant) can have significant positive effects on pain levels in PLWH[3].
This finding supports the promotion of less fragmented care in managing PLWH. There is a need for consistent empathetic care in health systems[3].
Physiotherapists are well trained and positioned to provide such a relationship. In low-resource or rural settings, this role could be filled by training community healthcare workers (CHWs) [3].
Other
Massage: There is low to moderate evidence to support the use of massage in PLWH. It may improve quality of life, but it has not been shown to have any effect on pain on activity levels. Given the lack of evidence, it could be useful as a self-management/care-giver tool, but should not be the focus of pain management programmes/interventions[22].
Splinting: Night splinting for neuropathic pain has not been found to be effective[7]
The Role of Physiotherapy
Physiotherapists can play a very important role in the management of pain in PLWH
Biopsychosocial Approach to Pain Management in HIV[11]Exercise - Physiotherapists are experts in exercise prescription. They can assess patients' physical status, help design appropriate strengthening and aerobic exercise plans and monitor progress in physical function.
Biopsychosocial approach - chronic pain is complex and requires a holistic approach, especially with the added biological, psychological and social complications that PLWH face. Physiotherapists have the knowledge and communication skills to identify core contributing factors that influence pain[11].
Goal setting and motivation - Through motivational interviewing, encouragement and goal directed management plans, physiotherapists can assist patients in achieving their functional goals
Therapeutic relationship - Physiotherapists often have more time with a patient and typically see patients at regular intervals. This makes them ideally positioned to build a strong trust relationship with PLWH, which has therapeutic benefits.
Training of CHWs - In low resource/rural settings physiotherapists can play an important role in training mid-level community workers in implementing simple, yet effective, self-management programmes for PLWH in their community.
Education - Physiotherapists, especially those trained in chronic pain management, have an in-depth understanding of pain physiology and pain management strategies. They can act as facilitators in delivering group education interventions, or provide one-on-one information patients.
The Multi-Disciplinary Team (MDT)
The complexity of chronic pain, especially in PLWH, ultimately requires an integrated team approach - with the patient at the centre.
Medical doctors - Ensure early initiation on ART, and adjust medication as needed. Prescription of medication for pain, based on underlying pain mechanisms, in conjunction with referral to pain and rehabilitation team members.
Nurses - Screening for chronic pain; Monitoring adherence and the effect of interventions
Public Health Practitioners - Continuous research into the most cost-effective and contextually appropriate interventions; promoting health and advocating for policies that ensure integrated care models are in place for PLWH - with particular focus on addressing stigma and mental health (contributors to pain)
Occupational therapists - Assist with functional goal setting and coping strategies, as well as mental health interventions
Psychologists - Counselling and facilitation of support groups
Health care workers need to collaborate and communicate to ensure PLWH are receiving the comprehensive care that their condition requires, and which they deserve.
↑ 1.01.11.21.31.41.51.6Berg LS, Young JJ, Kopansky-Giles D, Eberspaecher S, Outerbridge G, Hurwitz EL, Hartvigsen J. Musculoskeletal Conditions in Persons Living with HIV/AIDS: A Scoping Review. Current Medical Science. 2022 Feb;42(1):17-25.
↑ 5.05.1Nkhoma K, Norton C, Sabin C, Winston A, Merlin J, Harding R. Self-management interventions for pain and physical symptoms among people living with HIV: a systematic review of the evidence. JAIDS Journal of Acquired Immune Deficiency Syndromes. 2018 Oct 1;79(2):206-25.
↑ 11.011.111.211.311.411.511.611.7Slawek DE. People living with HIV and the emerging field of chronic pain—what is known about epidemiology, etiology, and management. Current HIV/AIDS Reports. 2021 Oct;18(5):436-42.
↑Augustine TN, Cairns CJ, Chetty S, Dannatt LG, Gravett N, Grey G, Grobler G, Jafta Z, Kamerman P, Lopes J, Matsabisa MG. Priority areas for cannabis and cannabinoid product research in South Africa. African Journal of Primary Health Care & Family Medicine. 2018;10(1):1-3.