When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Aspergillus is a fungus found throughout the world that can cause infection in primarily immunocompromised hosts and individuals with the underlying pulmonary disease. Many different species of Aspergillus can cause infection.
There are three major types of bronchopulmonary Aspergillus infections and an emerging 4th entity:
Coronavirus disease–associated pulmonary aspergillosis (CAPA), detected recently through reports, primarily from centres in Europe (as an emerging entity).[1]
If left untreated, invasive aspergillosis can have mortality approaching 100%.
In cases of suspected invasive aspergillosis treatment should be initiated early to reduce morbidity and mortality.[2]
Image: Pulmonary invasive aspergillosis in a person with interstitial pneumonia (autopsy material), using Grocott's methenamine silver stain.
Epidemiology
Aspergillus species are common - Aspergillosis complicating severe influenza infection has been increasingly detected worldwide[1].
Those working in the construction and farming industries may be at increased risk of Aspergillus infection due to chronic exposure in their work environments. Smoking marijuana contaminated with the fungus may also place an individual at risk for infection. Nosocomial Aspergillus infections have been reported from hospital showers and healthcare facilities undergoing construction[2]
Invasive aspergillosis:
Common only in the immunocompromised population, composed of patients with AIDS, neutropenic patients, those on long-term corticosteroids, and recipients of transplants on anti-rejection medications. The incidence of aspergillosis in patients undergoing bone marrow transplantation can be as high as 10% to 20%.
Also be seen in the critically ill intensive care patient with an underlying pulmonary disease such as chronic obstructive pulmonary disease (COPD) or asthma.
Incidence of invasive aspergillosis has risen four-fold in the last 13 years.
2. Chronic aspergillosis:
Patients with underlying lung diseases such as chronic obstructive lung disease, tuberculosis, asthma, lung cancer, and sarcoidosis are also at higher risk for developing the chronic form of aspergillosis.
3. Allergic bronchopulmonary aspergillosis:
Almost exclusively found in asthma and cystic fibrosis patients.
4. Aspergillosis may occur in the setting of severe influenza infections even among immunocompetent hosts.
Risks may include influenza A (H1N1) or B infections and viral-induced lymphopenia.[3]
Aspergillosis is a complication of COVID-19 in a significant minority of critically ill hospitalized patients, failure to recognize or diagnose the disease will likely lead to excess mortality[1].
Pathophysiology
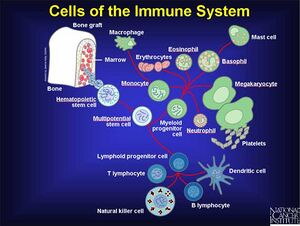
In an otherwise immunocompetent person, Aspergillus conidia are inhaled and taken up by phagocytes in the lungs.
The conidia (spore) germinate into hyphae (the filaments or threads composing the mycelium of a fungus[4]) at body temperature.
In immunocompetent hosts, phagocytes secrete mediators which activate neutrophils.
Neutrophils kill the invasive hyphae, and the Aspergillus infection is kept at bay.
If any of these mechanisms are impaired in an immunocompromised patient, the infection may be allowed to spread[2]
Assessment
A thorough history and physical exam should be done in every patient suspected of having an aspergillus infection.
Care should be taken to understand a patient’s risk factors for invasive diseases, such as immunocompromised status.
Invasive aspergillosis patient
Often be a critically ill person with immunocompromised status. This condition should also be considered in an already critically ill patient with underlying lung disease.
Most common initial symptoms include dyspnea, increased sputum production, chills, headache, and arthralgias.
As the condition quickly progresses, fever, toxicity and weight loss manifest.
On examination, there may be sinus tenderness, nasal discharge, rales, dermatologic changes, or meningeal signs of the central nervous system.
2. Chronic pulmonary aspergillosis
Presents most commonly with chest pain, weight loss, cough, hemoptysis, shortness of breath, and fatigue.
3. Allergic aspergillosis
Present with recurrent exacerbations of asthma with the most prominent finding being dyspnea and wheezing along with coughing up large amounts of sputum with brown[2]
Involves a group of techniques, aimed at assisting the removal from the lungs of excess secretions (or sputum, mucus, phlegm). It can be used to improve ventilation of the lungs, assist a cough and to reeducate breathing muscles. eg:
Treatment of suspected invasive aspergillosis should be initiated promptly as the patient's condition can decline quickly over 1 to 2 weeks from onset to death.
Intravenous therapy for critically ill patients with appropriate medications (eg antifungal medications) are initiated. Consideration should also be taken to resolve the patient's immunocompromised state as much as possible considering their comorbid conditions.
Treatment of patients with chronic pulmonary aspergillosis who are exhibiting pulmonary symptoms and loss of pulmonary function is accomplished with oral therapy anti fungal medications. A minimum of 6 months of therapy for all patients is recommended, though lifelong therapy for patients with the chronic progressive disease may be necessary. Failure of outpatient therapy usually requires hospital admission for intravenous (IV) therapy.
Surgery along with antifungal therapy may be required to remove an aspergilloma. This approach is most effective in patients who have a single lesion and not diffuse disease.
Antifungal prophylaxis with antifungal medication is recommended for patients with prolonged periods of neutropenia from chemotherapy, lengthy radiation treatments, allogeneic stem cell transplant recipients, severe or prolonged graft-versus-host disease, and solid organ transplant recipients.
Allergic bronchopulmonary aspergillosis exacerbations are typically treated with a 3 to 6-week course of oral corticosteroids in addition to itraconazole[2].
Prognosis
Aspergillosis is a benign infection in immunocompetent individuals but it carries a very grave prognosis in transplant patients and those who are immunocompromised.
Despite intensive antifungal therapy, the mortality remains high. Immunocompromised patients tend to have the highest mortality. Even those who are treated, tend to have a high recurrence rate. Once the infection has spread to the CNS, the mortality is close to 100%.
The high mortality in these patients has been blamed on resistance to the antifungal medications[2].
The Future
What will be the diseases caused by Aspergillus in 2030?
The number of immunocompromised patients with more complex immune and metabolic abnormalities will increase in the near future.
Consequently, the number of Aspergillus infections will continue to increase, especially if worldwide antifungal resistance emerges.
The morbidity of tuberculosis and malaria is much higher than that of invasive aspergillosis, with aspergillus, 50% or more of the patients die of the disease, whereas only 12% and 0.2% die from tuberculosis and malaria, respectively.[5]