When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Cerebral visual impairment (CVI) can occur in children with cerebral palsy (CP) or developmental delay.[1] Children with CVI are frequently diagnosed with cerebral palsy. Despite the importance of early diagnosis, there is no standardised assessment tool to diagnose CVI. Nor is there one referral criteria guideline.[1] The challenge in early diagnosis relates to the wide range of visual dysfunctions present in CVI. These include central and peripheral vision dysfunction, dysfunctions in movement perception, gaze control, visual guidance of movement, visual attention, attentional orientation in space, visual analysis and recognition, visual memory and spatial cognition. These impairments can all affect a child's learning and social interactions.[2] This article presents an overview of CVI and its relationship with cerebral palsy.
Definitions
Cerebral Visual Impairment
Cerebral Visual Impairment (CVI) is “a verifiable visual dysfunction, which cannot be attributed to disorders of the anterior visual pathways or any potentially co-occurring ocular impairment.”[3]
Cerebral Palsy
Cerebral Palsy (CP) "describes a group of permanent disorders of the development of movement and posture causing activity limitation, which is attributed to non-progressive disturbances that occurred in the developing fetal or infant brain."[4]
Brain Involvement in Vision
"It is estimated that over 50% of the brain is involved in vision processing."[5] -- Angela Kiger
The following example of a child catching a ball explains how the brain controls eyesight.[5][6][2]
The child sees the ball.
The frontal lobe decides on the action of catching the ball and its strategy.
The occipital lobe processes the information received through the eyes. It passes the processed image data to the posterior parietal lobes via the superior longitudinal fasciculi.
The middle part of the temporal lobe supports this process, with the posterior thalamus and superior colliculi, facilitating visual search and visual guidance of movement.
The ball is identified and chosen as the target.
The parietal lobe gauges the distance between the child's hands and the ball. If this is not the child's first time catching a ball, the temporal lobe takes part in the process as it controls memory. It subconsciously reminds the child that their hands are used to catch a ball, that they need to reach out, and that their body needs to adjust.
The temporal lobes process local and detailed visual feedback via a bundle of nerve fibres on each side.
The cerebellum helps the child adjust the timing of their actions and their balance.
Epidemiology
CVI affect at least 3.4% of children. However, the number may be higher as many affected children go unidentified.[7]
More than 50% of children with learning difficulties who attend special schools have CVI.[7]
CVI is present in 2 per 1000 live births. It is present in 19 per 1000 live births for infants born at 20-27 weeks gestation; subcortical damage is more common in preterm infants.[8][9]
It is the most common cause of permanent vision loss in children aged 1-3 years old.[5]
Almost 50% of children diagnosed with a visual impairment have CVI. [5]
56% of individuals with CVI have additional disabilities.[5]
Aetiology
CVI in children can occur in the prenatal, perinatal or postnatal periods.[10]
Brain damage in patients with CVI can be categorised as subcortical, cortical or both. Brain lesions resulting in CVI can affect the following parts of the brain:
the posterior visual pathways (the visual cortex of the occipital lobe)
the optic chiasm ("part of the brain where the optic nerves cross"[11])
lateral geniculate bodies (a structure in the thalamus)
optic radiations ("key white matter structures that cross the temporal lobe"[12])
primary visual cortices (part of the occipital lobe that processes visual information)
the middle temporal lobes
the visual association areas
The following video explains the role of the visual association areas:
In medically-based CVI classification, most children with CP belong to the B subgroup.[20]
The lesions which determine motor deficits in CP are "anatomically closely located to the distributed network of brain areas responsible for visual perception", and this helps explain the co-occurrence of CVI and CP.[21]
The clinical spectrum of visual problems in children with CP is broad, ranging from mild to severe. It may include ophthalmological, oculomotor, basic visual function, and cognitive-visual disorders.[20]
The intensity of visual impairment correlates with the severity of motor deficits:[22]
altered stereopsis ("the ability to appreciate depth, due to the lateral displacement of the eyes providing two slightly different views of the same object"[23]).
less frequent oculomotor involvement
less frequent refractive errors
Assessment and Diagnosis
Admission Referral
Children are often referred to a specialist or specialists for assessment of visual impairment because:[1]
the parents are concerned about the child's visual functioning
they have an increased risk of CVI
they have an intellectual disability or syndrome and can be screened for visual functioning
Multidisciplinary Team
A multidisciplinary team for CVI diagnostics is necessary for accurate and timely diagnosis. The team should include the following specialities at the minimum:
paediatric ophthalmologist
paediatric neurologist
orthoptist or optometrist
neuropsychologist
Follow-up Referral
The assessment results should be discussed with all members of the multidisciplinary team. Based on the outcome, the child can be referred to:[1]
vision teacher and developmental therapist with a vision specialisation in CVI
a rehabilitation centre or a specialised centre
school for children with visual impairments if there is evidence of CVI
Assessment Tools
There is no standardised assessment tool for the diagnosis of CVI. The following assessment tools are recommended:[24]
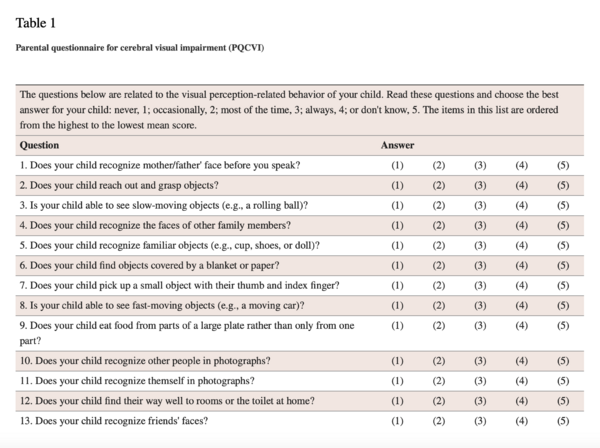
Reproduced from reference: Moon JH, Kim GH, Kim SK, Kim S, Kim YH, Kim J, Kim JK, Noh BH, Byeon JH, Yeom JS, Eun BL, Eun SH, Choi J, Chung HJ. Development of the Parental Questionnaire for Cerebral Visual Impairment in Children Younger than 72 Months. J Clin Neurol. 2021 Jul;17(3):354-362.Questionnaires
Parental Questionnaire for Cerebral Visual Impairment (PQCVI) (see figure)
The Five Questions completed by a parent. A 5-point Likert Scale describes if the child ‘always’, ‘often’, ‘sometimes’, ‘rarely’, or ‘never’ struggles with the described tasks[25]
Functional vision assessment (CVI Range)
"Behavioural assessment of functional vision, which defines the ability to interpret and react to visual information"[26]
assessment based on observation, parent interview and direct assessment
the evaluator grades the child on ten characteristics of CVI:[26]
colour preference
need for movement
visual latency
visual field preferences
difficulties with visual complexity
need for light
difficulty with distance viewing
atypical visual reflexes
difficulty with visual novelty
absence of visually guided reach
scores range from 0 to 10 when 0 represents no functional vision, and 10 means typical or near typical functional vision
Neuropsychological assessment of children with possible CVI
↑Sakki HEA, Dale NJ, Sargent J, Perez-Roche T, Bowman R. Is there consensus in defining childhood cerebral visual impairment? A systematic review of terminology and definitions. Br J Ophthalmol. 2018 Apr;102(4):424-432.
↑Rosenbaum P, Paneth N, Leviton A, Goldstein M, Bax M, Damiano D, Dan B, Jacobsson B. A report: the definition and classification of cerebral palsy April 2006. Dev Med Child Neurol Suppl. 2007 Feb;109:8-14. Erratum in: Dev Med Child Neurol. 2007 Jun;49(6):480.
↑ 5.05.15.25.35.45.5Kiger A. Cerebral Visual Impairment and Cerebral Palsy Course. Plus, 2023.
↑Robertson CM, Watt MJ, Dinu IA. Outcomes for the extremely premature infant: what is new? And where are we going? Pediatr Neurol. 2009 Mar;40(3):189-96.
↑Macintyre-Béon C.Cerebral Visual Impairment in Children Born Prematurely. A thesis submitted to the University of Glasgow for the degree of M.Sc. (Med) Nursing and Health Care (Research).College of Medical, Veterinary and Life Sciences University of Glasgow 2015
↑Chang M, Borchert M. Methods of visual assessment in children with cortical visual impairment. Current Opinion in Neurology, 2021; 34(1):p 89-96.