When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Bleck’sHeel Bisector Line (HBL) is a simple measure that assesses the flexibility and severity of metatarsus adductus. It is a manual assessment. No special equipment is needed to complete this assessment. This method has been used for over four decades, with some modifications. However, recent research has shown that this method can be unclear and has the potential for measurement errors when measuring the heel bisector line (HBL).[4] The procedure is as follows.
The shape of the weight-bearing foot is obtained. Traditionally, a mould of the weight-bearing foot is made; modifications include using footprints or photos of the weight-bearing foot.[4] Another option includes placing the child in prone with their knees flexed to 90 degrees and the plantar surface of the foot parallel to the ceiling.[2]
The procedure is completed by determining the longitudinal axis of the ellipse with a straight edge, independent of the forefoot.[4]
According to Bleck’s method, classification depends on where the HBL crosses the metatarsal heads (see table above).[4]
Transmalleolar Axis Bisector (TMAB) is a newly proposed alternative assessment technique for measuring the severity of metatarsus adductus.[4] The procedure is described below.[4]
The child is in prone with their knees flexed to 90 degrees and the plantar surface of their foot parallel to the ceiling. Weight-bearing of the foot is approximated by maintaining the ankle in a plantigrade position.
Using a pair of vernier calipers, a line is drawn across the heel, connecting the most medial point of the medial malleolus to the most lateral point of the lateral malleolus. The midpoint of this line is marked.
A goniometer is then placed on the foot, with the axis on the marked midpoint and the stationary arm aligned on the drawn line. The moveable arm is placed at 90 degrees to the stationary arm. The moveable arm delineates the TMAB.
Classification of metatarsus adductus relates to where the TMAB crosses the metatarsal heads. There are currently no classification norms using this method as research is ongoing. Researchers recommend recording TMAB location results with descriptors such as "at the second interdigital web space" or "third digit" or "third interdigital web space."
Intervention
Mild cases: typically resolve without intervention[2]
Pes planus is "defined by the loss of the medial longitudinal arch of the foot where it contacts or nearly contacts the ground."[5] It can occur with or without further deformities of the foot and ankle.[6]
Pes planus can be divided into two types:
Flexible: where the medial longitudinal arch of the foot is present on heel elevation (tiptoe standing) and non-weight bearing but disappear with full weight bearing on the foot.[7] Most typically developing infants are born with flexible flat feet. Arch development is first seen around three years of age, with adult values in arch height developing between seven and ten years of age.[5][8]
Rigid: where the medial longitudinal arch of the foot is absent in both heel elevation (tiptoe standing) and weight bearing. This is normally associated with underlying pathology,[9] such as vertical talus or tarsal coalition.[6]
Congenital: most infants have flat feet due to ligamentous laxity and developing neuromuscular control. Only a small percentage of children fail to develop normal arches. Children with Down Syndrome, Marfan Syndrome, or Ehlers-Danos Syndrome can be prone to congenital ligamentous laxity.[5]
Acquired: most commonly associated with posterior tibial tendon dysfunction, which is most common in females over the age of 40 who have comorbidities, such as diabetes and obesity.[5]
Factors that can contribute to an increased flat foot:
Little time spent barefoot, resulting in weak foot intrinsic muscles and poor foot arch development.[2]
"... we don't need to correct if they don't have pain, if there's no problem with their gait, or their ability to participate in activities of interest. "
-Krista Eskay, PT[2]
Rehabilitation Interventions:
Pain management
Stretching/increasing ankle flexibility
Strengthening foot intrinsics and ankle muscles
Proprioceptive training
Family education and reassurance
Providing additional support:
Shoes with arch support: this will not correct the deformity but will provide additional stability and can result in improved mobility and gait
Orthotics
When to refer:
To an orthopaedist:
if the longitudinal arch of the foot is absent on heel elevation or is asymmetrical
there is significant pain affecting activities of daily living or mobility
To a neurologist:
abnormal neurological screen
if the child is under five years of age and has pain in their knees, hips and feet
To a physical medicine specialist:
if the child is under five years of age and has pain in their knees, hips and feet
Clubfoot "is one of the most common congenital malformations and is characterized across varying degrees and severity of predictable contractures manifesting with four main components: (1) midfoot cavus, (2) forefoot adductus, (3) heel/hindfoot varus and (4) hindfoot equinus."[10]
When assessing the foot, there are several distinctive deformities associated with clubfoot.[10][13]
Midfoot cavus
Forefoot adductus
Hindfoot varus
Hindfoot equinus
These malformations can present with a range of orthopaedic deformity and degree of stiffness.[10] Several scoring systems exist[2] and can be used to help in assessing and classifying the degree of deformity present. According to the literature, there is no gold standard grading method for assessing or monitoring the degree of deformity associated with clubfoot.[13]
Pirani Scoring System
The Pirani Scoring System is based on six well-described clinical signs of contracture characterising a severe clubfoot.[14] This scoring system quantifies the degree of clubfoot deformity.[15]
If the sign is severely abnormal, it scores 1
If it is partially abnormal, it scores 0.5
If it is normal, it scores 0
The midfoot and hindfoot are evaluated separately. The Midfoot Contracture Score (MFCS) includes the medial crease, lateral edge convexity (also called curved lateral border), and the lateral talus head position. The Hindfoot Contracture Score (HCFS) includes the posterior crease, empty heel, and rigid equinus.[15] The six areas assessed include three signs from the midfoot and three signs from the hindfoot. The six areas are scored as described above, then the scores are summed to a Total Score, which ranges from 0-6. The higher the score, the more severe the presentation.[14]
The assessment is performed with the examiner in sitting. The infant is on the mother’s lap. It is easier to perform a precise examination if the infant is feeding and relaxed. The measurements are made while the examiner gently corrects the foot with minimal effort, and no discomfort.[14] For more information on using this scoring system, please read this article. For a clinical example, please see this article
Dimeglio Classification Scoring System
Abbreviations for above: pltf = plantarflexion; dorsx = dorsalflexion; var = varus; vlg = valgus; sup = supination; pron = pronation; add = adduction; abd = abduction.
Dimeglio Classification Scoring System is based on 8-rated areas characterising clubfoot. It focuses on assessing the degree of rigidity of the foot.[15][16] This scoring system distinguishes four basic parameters: (1) equinosity in the sagittal plane, (2) varus deviation in the frontal plane, (3) deformation of the block calcaneus and forefoot, and (4) adduction of the forefoot in the horizontal plane, evaluated on a scale from 0 to 4 points.[15] Next, an additional four adverse symptoms are assessed: (1) posterior crease, (2) medial crease, (3) cavus deformity, and (4) calf hypotrophy (deviant muscle function). These four symptoms are rated one point each.[15]
The total score ranges from 0-20. The higher the score, the more severe the presentation.[16]
most severe: 16–20
severe: 11–15
moderate: 6–10
postural: 0–5
Interventions
"The purposes of clubfoot therapy are to achieve and maintain clubfoot correction, so that the patients have functional, painless, plantigrade feet with good mobility" - Ponseti and Campos, 2009[13]
The Ponseti Method is the gold standard treatment for clubfoot deformity. This treatment method was developed in response to the complications and poor outcomes that came with the surgical management of clubfoot.[17] Treatment occurs over two phases: treatment phase and maintenance phase.
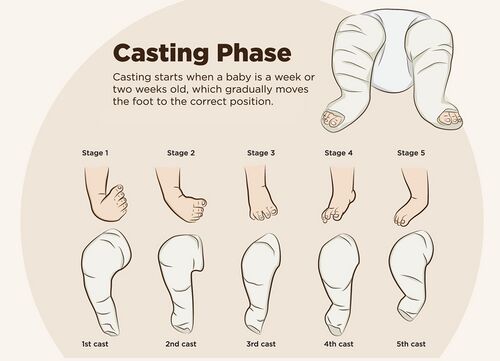
Treatment (Casting, Corrective) Phase is when the deformity is physically corrected by gentle mobilisations, and serial casting:[2]
begins as early in the infant's life as possible, typically within the first week
mobilisations and casting occur on a weekly basis
typically requires six[2] to eight[14] rounds of casting to correct the deformity
the majority of infants will still require minor surgery
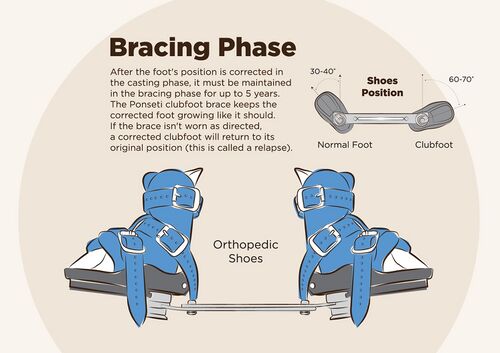
Maintenance (Bracing) Phase involves a strict and scheduled bracing protocol to prevent deformity reoccurrence as the infant continues to grow[2]
an orthotic brace must be worn for 23 hours per day for three months
the wearing schedule decreases to nightly for multiple years
adherence and carryover can be challenging for families to complete
inability to carryover properly and correctly in this phase in its entirety can result in recurrence of the clubfoot deformity
involves a complete cut through the Achilles tendon, not a tendon lengthening
the tendon heals sufficiently in approximately three weeks.
The procedures described above require advanced in-person training to perform them safely. It is not recommended that rehabilitation professionals perform serial casting without proper training due to the risk of pressure injury and wound formation. For a general overview of casting for clubfoot, please read this article.
Special Topic: The Role of the Rehabilitation Professional in Clubfoot Interventions
In addition to assisting in any part of the Ponseti Method, which requires advanced training, a rehabilitation professional has a large and important role to play in the effectiveness of clubfoot interventions.
Monitoring for clubfoot deformity recurrence: Approximately a third of infants who complete the Ponseti Method for the treatment of clubfoot will experience a deformity relapse. Rehabilitation professionals are integral to monitoring and reassessing the feet of these patients for signs of reoccurrence and to refer appropriately. Reassessment and supervision for clubfoot deformity recurrence needs to continue, potentially for many years following treatment, until the child is past their initial growth years.[18]
Family/caregiver training and support: The maintenance phase of clubfoot treatment can continue for many years and requires strict wearing of nighttime braces or orthotics. The family/caregiver is likely to face fatigue and decreased protocol carryover.[2] It is important to provide education and support on the possibility of late relapses.[18]
A 2020 study[19] found, especially in low- to middle-income countries, barriers such as (1) long travel distance and time to clinic, (2) lack of familial support, and (3) challenges with family's other commitments prevent treatment completion and increase drop-out rates. Providing support such as (1) appointment reminders, (2) family support groups and (3) financial support for travel and treatment have all been found to be effective in improving treatment completion.[19]
↑Squibb M, Sheerin K, Francis P. Measurement of the Developing Foot in Shod and Barefoot Paediatric Populations: A Narrative Review. Children. 2022 May 19;9(5):750.
↑ 14.014.114.214.314.4Africa Clubfoot Training Project. Chapter 4 Africa Clubfoot Training Basic & Advanced Clubfoot Treatment Provider Courses - Participant Manual. University of Oxford: Africa Clubfoot Training Project, 2017.
↑Gerlach, D.J., Gurnett, CA.,Limpaphayom, N.,Alaee, Farhang.,Zhang, Z.,Porter, K.,Smyth, M. D Dobbs, Matthew B 2009. Early results of the Ponseti method for the treatment of clubfoot associated with myelomeningocele. The Journal of bone and joint surgery. American volume, 91, pp.1350–1359