When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Exercise in the heat or cold can influence the body's ability to regulate body temperature. Although these processes are effective and well-functioning in normal conditions, in extremely hot or cold conditions thermoregulation (regulation of body temperature around a physiological set point) can be inadequate. The human body is able to adapt to these environmental thermal conditions with continued exposure over time. Acclimation refers to the body's short-term adaptations (days/weeks) to these environmental stressors, whereas acclimatisation refers to long-term adaptations (months/ years) to environmental stressors.
Regulation of Body Temperature
Humans are homeothermic - this means that the internal body temperature is physiologically regulated and kept nearly constant despite environmental temperature changes.[1]
Fluctuations in body temperature are usually no more than 1.0° C (degrees Celsius) or 1.8° F (degrees Fahrenheit)
Body temperature is a reflection of the balance between heat production and heat loss. If this balance is disturbed, there will be body temperature changes.[1]
Normal baseline range of body temperature is 36.1° to 37.8 C (97.0° - 100.0° F)
situations that will cause a change in normal baseline temperatures:
fever due to illness
extreme conditions of heat or cold
prolonged heavy exercise
Transfer of Heat between Body and Environment
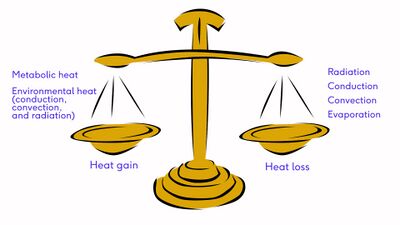
Figure 1. Thermoregulation ScaleMetabolic heat is produced by active tissues[1]
Heat moves from the body core (deep within the body) to the body shell (skin) via the blood
When the heat reaches the skin it can be dissipated by conduction, convection, radiation and evaporation
Maintaining a constant internal body temperature is dependent on the body's ability to balance heat gain (from metabolic processes and the environment) with heat loss. Figure 1. demonstrates this balance:
heat gain: metabolic heat and environmental heat (conduction, convection, radiation)
high humidity limits the evaporation of sweat as the air contains many H2O molecules
low humidity provides an ideal opportunity for evaporation
Prolonged sweat evaporation without adequate fluid intake can cause dehydration
Temperature of the skin is greater than the temperature of the environment = heat loss through conduction, convection and radiation and evaporation
Temperature of the environment is greater than skin temperature = heat can only be removed through evaporation
In hot humid situations, evaporation of sweat is limited and convection occurs from the environment to the skin (thus heat is gained)
Thermoregulatory Control
The body's thermoregulatory responses are very effective for normal ranges of body and air temperature. Core body temperature at rest is regulated at approximately 37° C (98.6° F). If the internal (core) body temperature exceeds 40° C (104°F), physiological function will be inhibited. Humans are able to briefly withstand core temperatures below 35° C (95° F) or above 41° C (105.8° F) .
Body's thermoregulatory centre - preoptic anterior hypothalamus (POAH)[3]
acts as a thermostat - monitors temperature and accelerates heat loss or heat generation when necessary
Sensory thermoreceptors provide information to POAH
skin - peripheral thermoreceptors
brain and spinal cord - central thermoreceptors
central thermoreceptors are more sensitive to temperature changes than peripheral thermoreceptors
When POAH senses deviation in body temperature (below or above normal), it sends signals through the sympathetic nervous system to the following thermoregulatory effectors[3]:
skin arterioles
POAH sends a signal via the sympathetic nervous system to smooth muscle in arteriole walls resulting in either vasodilation or vasoconstriction
vasoconstriction to minimise heat loss
vasodilation to enhance heat loss
eccrine sweat glands
sufficient rise in core and skin temperature - POAH sends a signal via the sympathetic nervous system to eccrine sweat glands, leading to active secretion of sweat. Read more on the Physiology of Sweat
endocrine glands
the effect of various hormones results in an increased cellular metabolic rate, and increased metabolism leads to an increase in heat production
skeletal muscle
increased skeletal muscle activity increases body temperature by increasing metabolic heat production
muscle actions can be voluntary or involuntary (for example when a person is shivering because of being cold)
Physiological Responses to Exercise in the Heat
Cardiovascular Response
Independent of the environment, exercise increases heat load due to muscle work and increased metabolism. The POAH sends signals via the sympathetic nervous system to the skin arterioles to vasodilate, which increases conductive and evaporative heat loss. Vasoconstriction occurs to direct blood from non-essential tissue such as the gut, liver and kidneys. Cardiac output further increases via an increase in heart rate and changes in contractility to maintain the blood supply to working muscle. Due to sweating, blood volume decreases and the ability to increase stroke volume is also limited due to peripheral blood pooling. Heart rate increases to compensate for the decrease in stroke volume (a phenomenon known as cardiovascular drift).[4]
Fluid Balance
Hot environmental temperatures and strenuous physical activity increase skin and core temperatures. The POAH controls the sweat glands. Sweat forms in the coiled section of the sweat gland and initially the electrolyte composition is the same as that of blood as plasma is the source of sweat formation. The filtrate of plasma moves through the duct of the sweat gland and sodium and chloride are reabsorbed back into the tissue and then into the blood. Thus, the sweat that is released onto the skin has fewer electrolytes than plasma.[4]
Light sweating - filtrate travels slowly through the duct, so there is more time for reabsorption of sodium and chloride and sweat is very diluted
Heavy sweating - there is less time for reabsorption of sodium and chloride as filtrate moves more quickly through the sweat duct, so the sodium and chloride content of sweat is higher
There is a difference in the electrolyte concentration of sweat in trained versus untrained individuals. With training and heat acclimation, more sodium and chloride are reabsorbed and sweat is more dilute. Concentrations of potassium, calcium and magnesium stay more or less the same. Exercise in hot and humid conditions can result in a loss of 2.5 % to 3.2 % of body weight through sweat. High rates of sweating reduce blood volume. This leads to an increased heart rate and eventually leads to a decrease in cardiac output and this affects athletic performance.[4]
Repeated exercise in the heat facilitates changes that improve performance in hot conditions.[10] This process is called heat acclimation (short-term 9 to 14 days) and acclimatisation (long-term months/years). The benefits of acclimation include[10]:
changes in sweating rate, sweat distribution and sweat content
cardiovascular function is optimised
lower core temperature during exercise
initial increase in plasma volume, this returns to normal levels after about 10 days
decrease in end-exercise heart rate and increase in cardiac output
this supports increased blood flow to the skin, which aids in greater heat loss and lowering of core temperature
widespread sweating earlier and sweat is more dilute
this prevents dangerous sodium loss and optimises evaporative heat loss
train in a similar hot environment to the competition (if the athlete is unable to do this, other methods such as overdressed training, passive heat exposure that increase the core and skin temperature can be used)
optimal duration of heat training to acclimate is 60 to 90 minutes per day for at least 2 weeks (consider that shorter duration can still lead to positive acclimation changes)
optimal frequency of heat acclimation sessions: at least 4 sessions per week to induce heat acclimation and 2 sessions per week to maintain heat acclimation.
Exercise in the Cold
Cold stress is any environmental situation that causes a loss of body heat and threatens homeostasis. A decrease in the skin or core temperature provides the POAH with information to activate various mechanisms to conserve body heat and increase heat production. These measures are[4]:
peripheral vasoconstriction
non-shivering thermogenesis
skeletal muscle shivering
behavioural responses such as putting on more clothes
Cold Habituation
Cold habituation occurs with regular exposure to repeated cold environments without significant heat loss. This is seen in vasoconstriction and shivering being blunted and the core temperatures dropping further than before the chronic exposure to cold.[12]
Metabolic acclimation occurs after repeated cold exposures with heat loss and enhanced metabolic and shivering heat production develop.[12]
Insulative acclimation occurs when an increase in metabolism cannot prevent heat loss. In this scenario, enhanced skin vasoconstriction occurs and this increases peripheral tissue insulation and reduces heat loss.[12]
muscle fibre recruitment is altered and contractile forces are reduced
muscle shortening velocity and power decreases
large deep muscles are not affected as much as superficial muscles
With an increase in fatigue there is also a decrease in metabolic heat production and during endurance exercise, the depletion of the athlete's energy reserve may be a potential risk for hypothermia.
If the body's core temperature drops below 34.5° C (94.1° F) the POAH loses its ability to regulate body temperature. At body temperatures of 29.5° C (85.1° F), the POAH has completely lost the ability to thermoregulate and metabolism slows and there is a loss of function that leads to drowsiness, lethargy and even coma.
Low core body temperature affects the sino-atrial node of the heart and decreases heart rate.
Breathing cold air does not damage the ventilatory tissue, as inhaled air is progressively warmed as it moves through the respiratory tract. Extreme cold will reduce ventilation (decreased respiratory rate and volume).
Treatment for mild hypothermia:
remove the individual from the cold
provide dry clothing, blankets and warm beverages
Treatment for severe hypothermia
gentle handling to avoid cardiac arrhythmias
gradual rewarming, hospital facilities and medical care is necessary
↑Griggs KE, Stephenson BT, Price MJ, Goosey-Tolfrey VL. Heat-related issues and practical applications for Paralympic athletes at Tokyo 2020. Temperature. 2020 Jan 2;7(1):37-57.
↑ 4.004.014.024.034.044.054.064.074.084.094.10Kenney WL, Wilmore JH, Costill DL. Exercise in Hot and Cold Environments. In Physiology of sport and exercise. Human kinetics; 2021 Oct 26.
↑Sawka MN, Burke LM, Eichner ER, Maughan RJ, Montain SJ, Stachenfeld NS, American College of Sports Medicine. American College of Sports Medicine position stand. Exercise and fluid replacement. Medicine and science in sports and exercise. 2007 Feb;39(2):377-90.
↑ 6.06.16.26.36.46.5Racinais S, Hosokawa Y, Akama T, Bermon S, Bigard X, Casa DJ, Grundstein A, Jay O, Massey A, Migliorini S, Mountjoy M. IOC consensus statement on recommendations and regulations for sport events in the heat. British Journal of Sports Medicine. 2023 Jan 1;57(1):8-25.
↑Nowak AS, Kennelley GE, Krabak BJ, Roberts WO, Tenforde KM, Tenforde AS. Endurance athletes and climate change. The Journal of Climate Change and Health. 2022 Feb 1:100118.
↑ 12.012.112.2Yurkevicius BR, Alba BK, Seeley AD, Castellani JW. Human cold habituation: Physiology, timeline, and modifiers. Temperature. 2022 Apr 3;9(2):122-57.
↑Castellani JW, Eglin CM, Ikäheimo TM, Montgomery H, Paal P, Tipton MJ. ACSM expert consensus statement: injury prevention and exercise performance during cold-weather exercise. Current Sports Medicine Reports. 2021 Nov 1;20(11):594-607.