When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Carpal tunnel syndrome (CTS) is a common neurological disorder. The cases of CTS are on the rise as its incidence in the working population can reach 8%.[1] Carpal tunnel syndrome is considered an occupational hazard, and production workers, material movers, and office administrative staff are at-risk occupations. Activities that involve excessive engagement of wrist flexion or prolonged wrist movements can lead to median nerve injury. [1] Treatment options include conservative measures or surgery.
This article discusses the anatomy and pathophysiology of CTS along with treatment considerations.
What is Carpal Tunnel Syndrome
Carpal tunnel syndrome is an entrapment or compression of the median nerve at the wrist as it passes through the carpal tunnel.[2] It is the most common compressive neuropathy and is more common in females.[3] Symptoms occur in the thumb, index finger, middle finger and the radial half of the ring finger. Early symptoms include:
Pain
Numbness and tingling
Paraesthesia
Can also lead to burning symptoms
Clinically Relevant Anatomy
Anatomy of the Carpal Tunnel
Some clinically relevant anatomical structures include[4]:
The carpal tunnel is a U-shaped, osteofibrous canal
The floor of the tunnel is formed by the carpal bones, and the roof by the flexor retinaculum
The tunnel is located deep to the flexor retinaculum / transverse carpal ligament, between the tubercles of the scaphoid and trapezoid on the lateral side and the pisiform and hook of hamate on the medial side
The four main structures passing through the tunnel are:
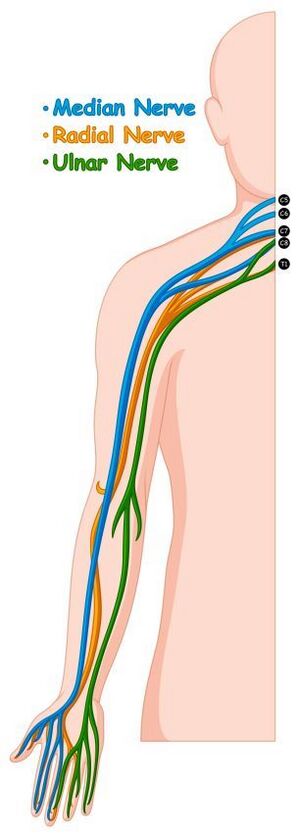
Begins in the axillary region with the root of median nerves situated in the anterior rami of C5-T1
The median nerve is formed by fascicles of the medial and lateral cords of the brachial plexus
Runs distally in the arm next to the brachial artery until the middle of the arm and descends into the cubital fossa (anterior elbow)
Principal nerve supply to the anterior compartment of the forearm
The muscular branch in the forearm supplies all the superficial and intermediate layers of the forearm flexors, except for flexor carpi ulnaris. These muscles are:
The terminal branch of the median nerve enters the hand through the carpal tunnel, along with the tendons of flexor digitorum profundus, flexor digitorum superficialis and flexor pollicis longus
Distal to the carpal tunnel, the nerve supplies five intrinsic muscles in the thenar part
The median nerve supplies sensation to the skin on:
The entire palmar surface
The sides of the first three digits
The lateral half of the fourth digit and
The dorsal aspects of the distal halves of these digits
Innervation to the thenar eminence includes flexor pollicis brevis, opponens pollicis and abductor pollicis brevis
Aetiology
Increased pressure in the carpal tunnel and compression of the median nerve is the main cause of carpal tunnel syndrome. The aetiology of carpal tunnel syndrome can be related to[5]:
Work
Lifestyle
Injury
Genetic predisposition
History of repetitive wrist movement or exposure to vibrations or forceful angular motions such as typing, gaming, machine work
Specific conditions may also be associated with an increased risk for the development of carpal tunnel syndrome (CTS). These can include:
Diabetes. The hyperglycemic conditions cause tendon inflammation and prevent tendons from gliding past one another
Pregnancy. Fluid retention during pregnancy may increase pressure in the carpal tunnel.
Obesity
Rheumatoid arthritis. Inflammatory conditions can lead to synovial hyperplasia, which reduces the space in the carpal tunnel.
Fall on an outstretched hand (FOOSH) – this can displace the lunate bone, which can cause pressure in the carpal tunnel
CTS is more commonly seen in females, usually between 36 and 60. Females may be more susceptible than males to compression of the median nerve because of a smaller relative cross-sectional area of the carpal tunnel.
Pathophysiology
Increased interstitial pressure in the carpal tunnel due to various causes such as:
It is hypothesised that the compression of the median nerve leads to the development of local ischaemia, and this may cause demyelination of the nerve, resulting in clinical symptoms. Normal pressure in the carpal tunnel varies between 2 – 10 mmHg. Repetitive wrist motion causes fluctuations in carpal tunnel pressure. Wrist extension can result in a 10-fold increase in pressure, and wrist flexion can result in an 8-fold increase in pressure.[5]
Clinical Presentation
Symptoms can develop gradually over months, years or decades[6]
Symptoms may arise spontaneously, but not commonly[6]
Numbness
Tingling or pins and needles sensation in the median nerve distribution of the hand (thumb, index finger, middle finger and radial half of the ring finger)
Symptoms are worst at night or early morning (complaints of nocturnal burning pain) and are relieved by shaking of the hand[6]
As symptoms worsen, intermittent pain and numbness may be experienced during daytime activities such as driving, lifting, working on the computer
Increased symptoms with static gripping of objects such as a phone or steering wheel
As symptoms progress, increased tingling and numbness and burning pain in the hand may be reported[4]
If symptoms are left untreated, patients can complain of constant pain, hand swelling, difficulties with motor control and weakness and visible atrophy of the thenar eminence[4]
Sensory deprivation may also be present, resulting in clumsiness, weakness, loss of grip and pinch strength[6]
Differential Diagnosis
The process of differential diagnosis should consider all conditions which could potentially cause dysfunction of the median nerve, the brachial plexus, C5 to C8 nerve root systems and the central nervous system.[7] Conditions to consider can include[7]:
Electrophysical assessment (i.e., nerve conduction studies) can measure and examine median nerve dysfunction. This is useful when diagnosing carpal tunnel syndrome to assess nerve function and quantify damage to the nerve.[2]
There is a debate in recent literature, with traditionalists arguing that nerve conduction studies are the gold standard for confirmation of a carpal tunnel syndrome diagnosis and contemporary thinkers arguing that a diagnosis is possible based on clinical symptoms. Furthermore, even amongst traditionalists in favour of nerve conduction tests, there seems to be no consensus on the single best technique to be used.[4]
Neuromuscular ultrasound is a valuable tool to investigate carpal tunnel syndrome as it provides information on median nerve morphology and the surrounding structures.[9] Recent research highlights that (based on expert consensus) combining electrodiagnosis and ultrasound is more effective than using either modality on its own. In cases where electrodiagnostic studies are normal or unable to localise suspected carpal tunnel syndrome, ultrasound can add value.[10]
Magnetic Resonance Imaging (MRI) is becoming more popular as a diagnostic tool for carpal tunnel syndrome. It can define the deeper and lateral limits of the carpal tunnel in more detail than ultrasound. It has also been shown to provide objective and accurate information about the anatomy and pathologies of the carpal tunnel.[11]
X-ray is recommended to exclude other causes of wrist pain or bony pathology[12]
Physical Examination
The location of symptoms is key for diagnosis.[13]
Carpal compression test
Apply firm pressure directly over the carpal tunnel for 30 seconds.
The test is positive when paraesthesia, pain or other symptoms are reproduced
Can improve short-term pain and functional status in individuals with carpal tunnel syndrome[20]
Neurodynamic techniques are more effective than electrotherapy interventions in the improvement of function and more effective than surgery to improve pain[20]
Researchers argue that gliding exercises may improve symptoms.[21] The supporting theory is that gliding exercises may prevent or stretch adhesions around the tendons and median nerve and thus reduce oedema and increase venous return. This may result in reduced pressure in the carpal tunnel.[21]
Examples of tendon gliding exercises are shown below in the section on Surgical Management
There is conflicting evidence on the effectiveness of tendon gliding exercises as conservative management. This may be due to the methodological quality of studies and the fact that the exercise therapy intervention is often applied and assessed in association with other management approaches.[22] A Cochrane review (2012)[23], reported limited evidence to justify the use of exercise and mobilisation techniques as a conservative intervention for Carpal Tunnel Syndrome, but the authors did suggest that decision-making and consideration for the use of exercise and mobilisation techniques as an intervention should be based on the clinician's experience as well as the patient's preference.[23]
↑ 4.04.14.24.3Urits I, Gress K, Charipova K, Orhurhu V, Kaye AD, Viswanath O. Recent advances in the understanding and management of carpal tunnel syndrome: a comprehensive review. Current pain and headache reports. 2019 Oct;23(10):1-8.
↑Walker FO, Cartwright MS, Alter KE, Visser LH, Hobson-Webb LD, Padua L, Strakowski JA, Preston DC, Boon AJ, Axer H, van Alfen N. Indications for neuromuscular ultrasound: Expert opinion and review of the literature. Clinical Neurophysiology. 2018 Dec 1;129(12):2658-79.
↑Pelosi L, Arányi Z, Beekman R, Bland J, Coraci D, Hobson-Webb LD, Padua L, Podnar S, Simon N, van Alfen N, Verhamme C. Expert consensus on the combined investigation of carpal tunnel syndrome with electrodiagnostic tests and neuromuscular ultrasound. Clinical Neurophysiology. 2022 Jan 6.
↑Trillos-Chacón MC, Castillo-M JA, Tolosa-Guzman I, Medina AF, Ballesteros SM. Strategies for preventing carpal tunnel syndrome in the workplace: A systematic review. Applied Ergonomics. 2021 May 1;93:103353.
↑Huisstede BM, Fridén J, Coert JH, Hoogvliet P, European HANDGUIDE Group. Carpal tunnel syndrome: hand surgeons, hand therapists, physical medicine, and rehabilitation physicians agree on a multidisciplinary treatment guideline—results from the European HANDGUIDE Study. Archives of physical medicine and rehabilitation. 2014 Dec 1;95(12):2253-63.
↑ 23.023.1Page MJ, O'Connor D, Pitt V, Massy‐Westropp N. Exercise and mobilisation interventions for carpal tunnel syndrome. Cochrane Database of Systematic Reviews. 2012(6).
↑Sheereen FJ, Sarkar B, Sahay P, Shaphe MA, Alghadir AH, Iqbal A, Ali T, Ahmad F. Comparison of Two Manual Therapy Programs, including Tendon Gliding Exercises as a Common Adjunct, While Managing the Participants with Chronic Carpal Tunnel Syndrome. Pain Research and Management. 2022 Jun 8;2022.
↑Rehab Mhttps://www.youtube.com/watch?v=BSyip8aUsqIy Patient. Thumb opposition proprioception. Available from: http://www.youtube.com/watch?v=dMH0bHeiRNg [last accessed 20/06/2022]