When refering to evidence in academic writing, you should always try to reference the primary (original) source. That is usually the journal article where the information was first stated. In most cases Physiopedia articles are a secondary source and so should not be used as references. Physiopedia articles are best used to find the original sources of information (see the references list at the bottom of the article).
If you believe that this Physiopedia article is the primary source for the information you are refering to, you can use the button below to access a related citation statement.
Elbow injuries in athletes occur in many sports and in athletes of all ages and levels. These injuries can have various causes such as acute trauma or overuse. Injuries can also range from catastrophic to minor. An effective elbow management treatment plan should include the identification of the causative factors of the injury to guide the design of the management plan. It will also steer the rehabilitation progression plan in a systematic way, so the athlete can return to their prior level of function in an efficient and safe manner.[1]
A multi-disciplinary team approach is a crucial part of the management of elbow injuries. For positive outcomes, a systematic and phased approach is necessary to progress exercises and stresses applied to the elbow. This will enable restoration of joint mobility, movement, motor control, strength and stability around the joint, as well as the whole kinetic chain.[1]
With the translation of clinical information obtained in the assessment of an elbow injury, it is wise to consider the following quote: “Not everything that matters can be measured… and not everything that can be measured matters.”[2]
Rehabilitation Objectives
In the planning of a rehabilitation/management programme, it is necessary to consider both form and function and how these two go together in the management of an athlete with elbow pain.
Consider and have a good understanding of the physiological knowledge of muscular strength vs muscular endurance and how / if this can influence the athlete's pain.
Exercise Prescription
Considerations with exercise prescription for the athlete with an elbow injury should include the following[2]:
The purpose of the intended exercise
Know what needs to be achieved – athlete expectations but also physiologically
Is the exercise or rehabilitation engaging?
It is important to keep the patient engaged and incorporate rehabilitation exercises into their already existing training programme where possible.
Time - efficient
Exercise Therapy
Exercise therapy has been shown to be effective in the management of elbow pain[3], either as a stand-alone treatment, or as part of a multimodal treatment plan.[4] In the literature, there is no clear indication that a specific exercise regime or type of exercise is the best approach. There are studies (specifically on lateral elbow tendinopathy) that give preference to eccentric exercises over concentric exercise, while other studies show no differences between concentric or a combination of concentric and eccentric exercise programmes.[4] Types of exercise therapy in the management of the sporting elbow can include[2][5]:
Isometric muscle contractions
Occur when tension is developed in the muscle without movement, therefore the muscle origin and insertion does not move and there is no change in muscle length
Isotonic muscle contractions
Concentric muscle contractions: the muscle produces enough force to overcome the external resistance. The muscle shortens and there is movement at the joint.[6]
Eccentric muscle contractions: the muscle lengthens while producing force. This happens because the external resistance moves in the direction opposite to the standard concentric (shortening) action.[6]
Isokinetic muscle actions
These muscle actions are characterised by constant velocity and can only be achieved in a laboratory or clinical setting. Specialised computerised equipment is necessary to maximise resistance at every angle of range of motion. Isokinetic contractions can be concentric or eccentric. These type of contractions and devices can help athletes perform exercises that simulate the actual speed and sport-specific activities.[6]
Although this is mostly used for clinical testing, isokinetic exercise can be a useful management tool in elbow rehabilitation. The muscles around the elbow joint can be strengthened through the full range of motion. The use of this method needs to have merit and one should be sensible when deciding for which type of patient and condition this will be beneficial.[2]
Croisier et al.[9] reported that an isokinetic eccentric exercise programme was more effective than a non-strengthening exercise programme in patients with lateral epicondylalgia.
Isotonic
Examples of isotonic elbow strengtheningAlways consider the aim of the exercise
Is the aim muscle strength, muscle endurance or pain relief?
The position of the forearm neutral (thumb facing up) - brachioradialis is the main flexor of the elbow in this position
Forearm supination - Biceps Brachii comes more into play and is also a supinator of the forearm
Effect of forearm position on elbow extensors:
Forearm in pronation or supination makes no difference on elbow extensors – there is no mechanical advantage as the triceps inserts onto the olecranon.
However, the hand and wrist can play a role. In a supinated forearm position, there is not as much mechanical advantage for the hand and wrist as in a pronated position. Therefore, when performing elbow extension exercises to strengthen triceps, a way to isolate the triceps more is to perform the exercises with the forearm in supination. With the forearm in pronation, an elbow extension exercise may be easier, due to the mechanical advantage gained by the wrist flexors.[2]
Rehabilitation can be done with a fixed wrist with elbow movements or using wrist movements
The type of sport and the type of action needed is important to consider with exercise therapy and when determining which joints need to move
With forearm movements such as supination or pronation it is necessary to consider the importance of the proximal radioulnar joint in conjunction with the distal radioulnar joint in rehabilitation
The addition of leverage to an exercise can influence the radiocarpal joint i.e. holding a tennis racquet or golf club. It can also influence mobility and stability around the area - think about the addition of extra weight and the influence it can have on eccentric control[2]
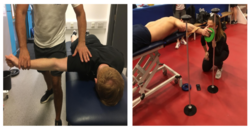
Include the shoulder complex in the management plan[10]:
Overhead athletes often lose internal rotation and horizontal adduction range of motion. For these athletes, an 18° loss of internal rotation in the throwing shoulder can lead to elbow injuries.[1]
A loss of external shoulder rotation range of motion may cause increased strain on the medial elbow during throwing.[1]
Always consider the context and the available technology in a specific sport i.e. punch trackers in boxing[2]
Exercise Therapy - wrist vs elbow
Forearm position in elbow strengthening
Consider shoulder in elbow rehabilitation
Other Management Strategies
Joint Mobilisation
Passive joint mobilisation
Consider the use of mobilisation techniques in stiff elbows after surgery or traumatic injuries
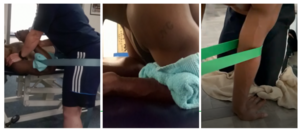
Examples of passive elbow joint mobilisationsMulligan’s mobilisation with movement (MWM) with the use of a belt is often used in the management of elbow injuries. However, in a recent systematic review on the effectiveness of Mulligan’s mobilisation with movement on peripheral joints, low-quality evidence was available for lateral epicondylalgia. Mobilisation with movement was reported to be superior to placebo and no-intervention control groups, but not superior to corticosteroids and other physiotherapy interventions.[11] Research also shows that the addition of MWM along with eccentric exercises improves pain and functional activities in people with lateral elbow tendinopathy.[12]
Joint mobilisations directed at the elbow can improve pain and functional grip scores in individuals with lateral epicondylalgia, but higher-quality studies are needed.[13]
In post-traumatic stiff elbows, there are anecdotal accounts that passive elbow mobilisations may lead to heterotopic ossification and a mechanical block to movement. Although studies have shown a relationship between forced movement and heterotopic ossification, it is important to note that these types of forceful manoeuvres “bear no resemblance to the passive mobilisations used by physiotherapists to address post-traumatic stiffness”.[14]
Using theraband to improve elbow flexionUsing exercises is a good way to actively mobilise the elbow joint
Find creative ways to gain range of motion for movements such as flexion and extension
Consider the use of long and short levers in active mobilisation of the elbow joint:
Especially in the early stages of rehabilitation of a condition where mobilisations are necessary, the patient can be given some autonomy in their rehabilitation with some easy exercises.
Active elbow mobilisation with TherabandExamples of using equipment to actively facilitate joint mobilisation
To improve elbow flexion range of motion: instead of using a free weight and open-chain elbow flexion and extension exercise with a longer lever, consider using a light resistance band with elbows flexed and shoulders in 90 degrees abduction and pulling the band closer to the chin, thereby increasing flexion in the elbow.
Another example is using a resistance band assisting with increasing flexion range of motion, here the band will pull the elbow into more flexion.
As the patient progresses, the equipment can be changed to provide more resistance and make the exercise more difficult.
Pain Management, Stability and Proprioception
End of range control
Sometimes a patient with an elbow injury may be recovering well, but continues to have pain at the end of range of movements such as flexion and extension. Passive modalities such as taping can assist with pain management in these cases.[2]
Using resistance bands to improve end of range control is also useful.
Active forms of pain management can include:
Vibration – works well for pain management but also influences stability and proprioception.[17] It is also a way to desensitise the area.[2]
Different factors to consider with the return to play decision making include[22]:
Medical factors
Patient demographics
Symptoms
Personal medical history
Physical examination
Lab tests and/or imaging
Functional tests
Athlete’s psychological state
Potential seriousness of the condition
Sport risk modifiers such as:
Type of sport (collision sport vs non-contact sport)
Player position
Limb dominance
Competitive level (recreational vs professional)
Ability to protect the injured area (e.g. padding)
Decision modifiers
Timing and season
Pressure from athlete (athlete’s desire to compete)
External pressure (coach, parents)
Masking the injury (effective analgesia)
Conflict of interest (i.e. financial)
Fear of litigation (e.g. if restricted or permitted)
Various factors can influence progression i.e. pain, physical characteristics and psychological factors.[2]
General Guidelines on the Management of the Sporting Elbow
Some key points to consider in the management of the sporting elbow include[2]:
Consider physical qualities vs pain
Consider objective and objectivity
This will help to not prolong rehabilitation, but also identify the need for early or added intervention or referral to another member of the multidisciplinary (MDT) team
Consider management of the complete kinetic chain vs local management
Corticosteroid injections and/ or surgery (early vs late intervention)
Short vs long term considerations
Multidisciplinary team considerations – involvement and decision making that is in the best interest of the athlete
References
↑ 1.01.11.21.3Wilk KE, Arrigo CA. Rehabilitation of Elbow Injuries: Nonoperative and Operative. Clinics in Sports Medicine. 2020 Jul 1;39(3):687-715.
↑Lowdon H, Chong HH, Dhingra M, Gomaa AR, Teece L, Booth S, Watts AC, Singh HP. Comparison of interventions for lateral elbow tendinopathy: a systematic review and network meta-analysis for patient-rated tennis elbow evaluation pain outcome. The Journal of Hand Surgery. 2024 Jul 1;49(7):639-48.
↑Özdinçler AR, Baktır ZS, Mutlu EK, Koçyiğit A. Chronic lateral elbow tendinopathy with a supervised graded exercise protocol. Journal of Hand Therapy. 2023 Oct 1;36(4):913-22.
↑ 6.06.16.2Rivera-Brown AM, Frontera MD. Principles of exercise physiology: Responses to acute exercise and long-term adaptations to training. PM&R. 2012; 4: 797-804.
↑Song JS, Seffrin A, Yamada Y, Kataoka R, Hammert WB, Spitz RW, Wong V, Kang A, Loenneke JP. Can we improve exercise-induced hypoalgesia with exercise training? An overview and suggestions for future studies. Physical Therapy in Sport. 2023 Sep 1;63:67-72.
↑Westad K, Tjoestolvsen F, Hebron C. The effectiveness of Mulligan's mobilisation with movement (MWM) on peripheral joints in musculoskeletal (MSK) conditions: A systematic review. Musculoskeletal Science and Practice. 2019 Feb 1;39:157-63.
↑Syed AU, Darain H, Rana M. The effects of the addition of Mulligan mobilization with movement to exercise on elbow pain and function associated with lateral elbow tendinopathy. Journal of Bodywork and Movement Therapies. 2024 Oct 1;40:872-9.
↑Lucado AM, Dale RB, Vincent J, Day JM. Do joint mobilizations assist in the recovery of lateral elbow tendinopathy? A systematic review and meta-analysis. Journal of Hand Therapy. 2019 Apr 1;32(2):262-76.
↑Tyler TF, Thomas GC, Nicholas SJ, McHugh MP. Addition of isolated wrist extensor eccentric exercise to standard treatment for chronic lateral epicondylosis: a prospective randomized trial. Journal of Shoulder and Elbow surgery. 2010 Sep 1;19(6):917-22.
↑Tiwari M. Effectiveness of flex bar eccentric exercises versus progressive resistance exercises of wrist on pain, pain free grip strength and functional activities in sub acute tennis elbow. Indian J Physiother Occup Ther. 2018 Jul;12(3):28-32.
↑Gatt I. Hand and wrist injuries: a focus on boxing. A Comprehensive Guide to Sports Physiology and Injury Management E-Book: an interdisciplinary approach. 2020 Nov 13:315.




 Exercise Therapy - wrist vs elbow
 Forearm position in elbow strengthening
 Consider shoulder in elbow rehabilitation