
Triangular Fibrocartilage Complex Injuries
Original Editor - Kristen Mason
Top Contributors - Kristen Mason, Admin, Jess Bell, Kim Jackson, Laura Ritchie, Rachael Lowe, Lucinda hampton, Shauni Van Overstraeten, 127.0.0.1, Shaimaa Eldib, Evan Thomas, Tarina van der Stockt, Kai A. Sigel, WikiSysop, Wanda van Niekerk and Joseph Ayotunde Aderonmu
Introduction

The triangular fibrocartilage complex (TFCC) is a structure on the ulnar side of the wrist that transfers load between the lunate, triquetrum, and ulnar head, while providing stability to the wrist. Injury to the TFCC can occur acutely through trauma or develop gradually. TFCC injury often accompanies distal radius fractures.[1] Risk factors include forceful ulnar deviation and positive ulnar variance. Management ranges from conservative measures to surgical intervention.[2] Most TFCC injuries have a favourable prognosis with appropriate treatment.
Clinically Relevant Anatomy
The TFCC comprises the ligamentous and cartilaginous structures that separate the radiocarpal joint from the distal radioulnar joint. Its components include the triangular fibrocartilage disc, meniscus homologue, ulnocarpal ligament, dorsal and volar radioulnar ligament and extensor carpi ulnaris sheath. It is the main stabiliser of the distal radioulnar joint. The volar portion prevents dorsal displacement of the ulna and is tight in pronation. The dorsal portion prevents volar displacement of the ulna and is tight in supination. The TFCC also contributes to ulnocarpal stability.[4][5]
- Origin: medial border of distal radius
- Insertion: ulnar fovea and base of ulnar styloid (via dual-lamina system); carpal bones, including the lunate, triquetrum, hamate (via ulnocarpal ligaments and meniscus homologue)
- Vascular supply: the central disc is avascular; the peripheral blood vessels penetrate the TFCC margins
Aetiology
When the wrist moves into ulnar deviation, the TFCC experiences increased compressive loading, which is further intensified in the presence of positive ulnar variance. Sports activities, such as hitting a baseball, that require forceful ulnar deviation generate high loads across the TFCC.[5]
Clinical Presentation
Patients typically present with ulnar-sided wrist pain that worsens with activity, and may also report grip weakness, instability, or clicking sensations.[6] Injury mechanisms vary with sport-specific demands, including forced wrist extension (baseball slides), repetitive loading during batting (baseball),[2] and repetitive weight bearing in support and hanging positions (gymnastics).[7]
Diagnostic Procedures
Physical Examination

The TFCC is best palpated with the wrist in pronation. It is located between the flexor carpi ulnaris, ulnar styloid, and pisiform. Several tests may be included in the examination, including:
- Fovea sign: the therapist palpates into the soft space between the ulnar styloid, the flexor carpi ulnaris tendon, the volar surface of the ulnar head and the pisiform. Tenderness in this area indicates a positive test.
- Piano key test: the patient is positioned in sitting, with their forearm pronated on the table. The therapist stabilises the patient's distal radius and hand with one hand, and then presses down with a volarly directed force on the ulna with the other hand, allowing it to passively spring back like a piano key. The test is positive for dorsal radioulnar joint instability if there is pain or excessive laxity compared with the opposite side.
- TFCC compression test: ulnar deviation with the forearm in neutral reproduces symptoms.
- TFCC stress test: applying an axial load across the ulna with the wrist in ulnar deviation reproduces symptoms.
- Press test: the patient lifts themselves out of a chair using their wrists in an extended position. Pain indicates a positive test.
- Supination test/TFCC table lift test: the patient places their hands under a table (palms up) with their forearms supinated and tries to lift the table. A score of 5 or more on the Visual Analogue Scale indicates a positive test.[8]
- Grind test: axial compression is applied through the distal forearm while the patient pronates/supinates their forearm. Pain can indicate a degenerative process.[2]
Diagnostic Imaging
Radiographs may reveal avulsion of the ulnar styloid, scaphoid fracture, distal radial fracture, volar tilt of the lunate or triquetrum and ulnar variance. Triple injection arthrography can identify TFCC tears, but has low specificity. MRI has high sensitivity and specificity for identifying TFCC tears.
Classification
The Palmer classification divides TFCC lesions into traumatic (Type 1) and degenerative (Type 2) injuries. While this provides an anatomical description, it does not guide treatment decisions or predict outcomes.[9]
Outcome Measures
- DASH Outcome Measure
- Modified Mayo Wrist Score
- Activities of Daily Living Score[10][11]
Management / Interventions
Conservative Treatment
Initial management for TFCC injury includes rest, activity modification, ice, NSAIDs, and splint immobilisation for 3-6 weeks.[12]
Surgical Intervention
Surgical interventions are considered if conservative management is unsuccessful or when there is distal radioulnar joint (DRUJ) instability. Surgical interventions include arthroscopic procedures (repair or debridement), ulnar shortening osteotomy, or the Wafer procedure.[2]
Post-Operative Rehabilitation
Postoperative recovery time depends on the surgical approach used. Arthroscopic procedures generally require four to six weeks for recovery, while open surgical approaches typically need around three months. Following surgery, patients should be referred for hand therapy. The timing and duration of rehabilitation depends on the type of surgery and the individual surgeon's protocol.[2] Rehabilitation follows similar principles to conservative management, with progression guided by surgical procedure and healing timeframes.
Rehabilitation Exercises
The following exercise progression can be used for both conservative management and post-operative rehabilitation. Timing and intensity are adjusted based on pain levels, tissue healing, and surgical procedure (if applicable).
Passive Mobilisation
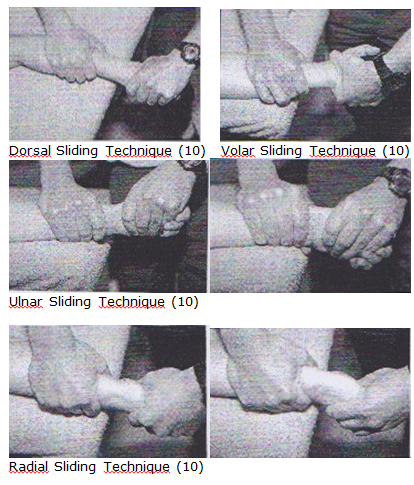
Gentle traction of the radiocarpal and the midcarpal joints can be applied:[13][14]
- a dorsal sliding technique can be used to promote wrist flexion
- a volar sliding technique can be used to promote wrist extension
- a ulnar sliding technique can be used to promote radial deviation
- a radial sliding technique can be used to promote ulnar deviation

General Mobility Exercises
Patients should perform general mobility exercises, including:[15][16][17]
- wrist flexion and extension
- horizontal ulnar and radial deviation
- pronation and supination
- stretching of the hand and finger muscles
Strengthening Exercises
When progressing to strengthening exercises, the following exercises can be performed with a weight or resistance band:[18]
- flexion and extension
- pronation and supination
Key Points
TFCC injuries cause ulnar-sided wrist pain. DRUJ stability determines management approach—stable injuries can trial conservative management for up to 6 months, while unstable injuries require surgical consultation. Treatment progresses from immobilisation through passive mobilisation to active strengthening.
References
- ↑ Im J, Kang SJ, Lee SJ. A comparative study between conservative and surgical treatments of triangular fibrocartilage complex injury of the wrist with distal radius fractures. Clin Orthop Surg. 2021 Mar;13(1):105-9.
- ↑ 2.0 2.1 2.2 2.3 2.4 Casadei K, Kiel J. Triangular fibrocartilage complex (TFCC) injuries. InStatPearls [Internet] 2020 Jan 20. StatPearls Publishing. Available from:https://www.ncbi.nlm.nih.gov/books/NBK537055/ (last accessed 5.4.2020)
- ↑ Marpole Physio What is a Triangular Fibrocartilage Complex Injury of the Wrist Available from: https://www.youtube.com/watch?v=pnk9cB9kMy8 (last accessed 5.4.2020)
- ↑ Verheyden JR, Palmer AK. EMedicine. Triangular Fibrocartilage Complex. http://emedicine.medscape.com/article/1240789-overview. (accessed 25 June 2009).
- ↑ 5.0 5.1 Wheeless CR. Wheeless' Textbook of Orthopaedics. Triangular Fibrocartilage Complex. http://www.wheelessonline.com/ortho/triangular_fibrocartilage_complex (accessed 25 June 2009).
- ↑ UK Orthopaedic Surgery & Sports Medicine. Health in Sports Report-Issue 6: Triangular Fibrocartilage Complex (TFCC) Injury. http://ukhealthcare.uky.edu/sportsmedicine/health_in_sports/issue6.asp (accessed 25 June 2009).
- ↑ Gymnastics Injuries TFCC Available from:https://gymnasticsinjuries.wordpress.com/tag/tfcc/ (last accessed 6.4.2020)
- ↑ Marcovici LL, Greco A, Chiossi B, Muscatiello AL, Tandioy-Delgado FA, Molayem I, Pagnotta A. The TFCC table lift test: A clinical tool for detecting palmer 1B TFCC lesions. J Hand Microsurg. 2025 Sep 2;17(6):100348.
- ↑ Sachar K. Ulnar-Sided Wrist Pain: Evaluation and Treatment of Triangular Fibrocartilage Complex Tears, Ulnocarpal Impaction Syndrome, and Lunotriquetral Ligament Tears. Journal of Hand Surgery. July 2012.
- ↑ Reiter A, Wolf MB, Schmid U, Frigge A, Dreyhaupt J, Hahn P, et al. Arthroscopic repair of palmer 1B triangular fibrocartilage complex tears. Arthroscopy. 2008;24(11):1244-1250.
- ↑ Estrella EP, Hung LK, Ho PC, Tse WL. Arthroscopic repair of triangular fibrocartilage complex tears. Arthroscopy. 2007;23(7):729-737.
- ↑ Parmelee-Peters, K., & Eathorne, S. (2005). The Wrist: Common Injuries and Management. Primary Care, Clinics in Office Practice, 35-70.
- ↑ Prof. Dr. R. Meeusen, Praktijkgids pols- en handletsels, VUB, p131-151.
- ↑ Wadsworth, C., The wrist and hand examination ans Interpretaion, J. Orthopedic and sports physical therapy, 1983, 108-20
- ↑ Leger AB, Milner TE. , Muscle function at the wrist after eccentric exercise, Medicine and Science in Sports and Exercise, 2001;33:612–20.
- ↑ Prof. Dr. R. Meeusen, Praktijkgids pols- en handletsels, VUB, p131-151.
- ↑ Wadsworth, C., The wrist and hand examination ans Interpretaion, J. Orthopedic and sports physical therapy, 1983, 108-20
- ↑ Prof. Dr. R. Meeusen, Praktijkgids pols- en handletsels, VUB, p131-151.